
Large terminal or interstitial deletions of the Xp22.3 region involving ANOS1 (KAL1) and adjacent genes results in “contiguous gene syndrome”. The rare co-occurrence of Kallmann syndrome and X-linked ichthyosis can be explained by this phenomenon. In this report, a case of Kallmann syndrome was described which is caused by deletion of exons 7–14 of ANOS1 gene due to an unbalanced translocation between chromosomes X and Y. This translocation resulted in 12.8 Mb duplication of Yq chromosome and 8.3 Mb deletion of Xp chromosome. Other clinically significant genes present in the deleted reion were STS, NLGN4X, ARSL (ARSE), SHOX, and VCX.
A 20 year old male (Figures 1A and B) was referred to the department of medical genetics of a tertiary care institute on the 16th of June, 2018. His chief complaints were delayed secondary sexual characteristics, impaired sense of smell, and poor scholastic performance. He was born of nonconsanguineous marriage. Family history was not significant. His weight was 60 kg (0 SD) and height was 151 cm (<−3 Z score). He had narrow palpebral fissures, eunuchoid appearance, gynecomastia, and sexual maturity rating corresponded to Tanner stage 3. His right testis was not identified in the scrotum or inguinal canal and left testicular volume was low (12 ml). Stretched penile length was 3.6 cm (<3rd centile). Mild ichthyosis on abdomen (Figure 1C) and back was observed. He did not have any significant facial dysmorphism or any other malformation. Central nervous system examination revealed hyposmia, hoarse voice, and synkinesia of hands.
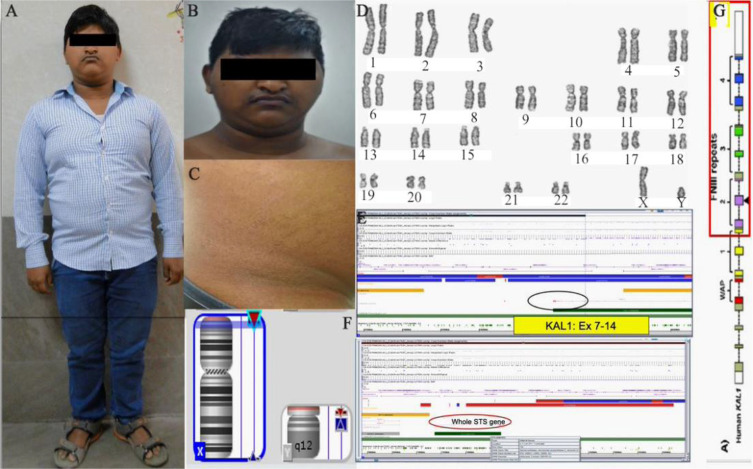
Endocrinological evaluation was suggestive of hypogonadotrophic hypogonadism [FSH: 0.733 IU/L, LH: <0.1 IU/L (normal value: 1.7–8.6) and testosterone: 5.59 nmol/L (normal value: 8.6–29)]. Skeletal survey did not reveal any significant findings. Karyotype from peripheral blood lymphocytes was performed and an extra material on p arm of chromosome X was identified (46,Xp+,Y) (Figure 1D). DNA was extracted from peripheral blood and cytogenetic microarray was performed by Cytoscan 750 K array kit (Affymetrix, USA). A 8.3 Mb deletion on short arm of chromosome X {arr[hg19] Xp22.33p22.31(168,551–8,538,809)} including 37 OMIM genes and a 12.8 Mb duplication on long arm of chromosome Y {arr[hg19] Yq11.221q11.23(15,999,473–28,799,654)}including 25 OMIM genes were identified (Figures 1E and F). The breakpoint on X chromosome resulted in deletion of important and clinically relevant genes including ANOS1 (KAL1) gene (7th–14th exon), STS gene, and 4 other genes including SHOX, ARSL (ARSE), NLGN4X, and VCX (Figure 1F). The duplicated Y segment contained only one clinically important gene namely, DAZ1. Duplication of DAZ1 has not been implicated in any disease causation. Parental blood samples were not available to identify the inherited characteristics of this chromosomal aberration. However, both parents were clinically normal and fertile.
Identification of contiguous gene syndromes has led to the establishment of chromosomal location of a number of disease loci. The Xp22.3 region is characterized by low frequency of interspersed repeats and a low GC content. This region contains several important genes including ANOS1 (KAL1), STS, PNPLA4, NLGN4X, ARSL (ARSE), SHOX, and VCX cluster (1). A large region of homologous sequences has been identified on Xp22.3 and Yq11 chromosomes. This sequence similarity often facilitates aberrant X–Y pairing during male meiosis and causes X–Y translocation. This in turn results in terminal or interstitial deletions of Xp22·3 region (2). The first case of X–Y translocation was observed in a female with reproductive failure (3) and in a male with severe mental retardation and short stature (4).
The preliminary investigation in our patient with karyotype revealed an extra material on the p arm of X chromosome. Cytogenetic microarray confirmed the origin of this material to be a duplicated segment of long arm of Y chromosome. It also delineated the exact region of breakpoint on the X chromosome due to this translocation and deletion of clinically important genes like ANOS1 (KAL1), STS, and other genes. The parents’ karyotype was not done but the derivative chromosome of this character is unlikely to be inherited as its presence will cause infertility in XX or XY individual. Individual with der(X), X will have phenotype of Klinefelter syndrome while a male with der(X), Y will be infertile like our patient.
The X-linked form of Kallmann syndrome was mapped to Xp22.3 region. Studies have described patients with variable deletions of distal short arm of chromosome resulting in complex clinical features combining Kallmann syndrome, X-linked ichthyosis, chondrodysplasia punctata, ocular albinism, short stature, and mental retardation (Table 1). In our study, the patient predominantly had clinical features of Kallmann syndrome and ichthyosis. Other clinical findings observed in our patient and the probable genes involved are tabulated (Table 2).
Table 1. Review of literature on clinical features of patients and molecular techniques used in contiguous gene syndrome
| Age | Karyotype | Techniques for delineation of chromosomal abnormality | Relevant Deleted genes | Hypo gonadism | Anosmia | Ichthyosis | CDP | XMR | Short stature | Deafness | Other abnormalities | Reference and year | |
|---|---|---|---|---|---|---|---|---|---|---|---|---|---|
| 9 years | 46,Y,del(X) (p22.3) | Southern blotting and pulsed field gel electrophoresis | CDPX1, STS, KAL, OA1 gene | + | + | + | + | + | + | − | Ocular albinism | Meindl et al (6) (1993) | |
| 13 years | |||||||||||||
| 14 years | Normal | PCR | STS KAL | + | + | + | − | − | − | − | Renal aplasia/hypoplasia | A Klink et al. (7) (1994) | |
| 41 years | |||||||||||||
| 23 years | Southern blotting for STS gene PCR for KAL1 gene | STS KAL (from 2nd exon ) | + | + | + | − | − | − | − | − | |||
| 19 | Not done | Southern blotting for STS gene | STS KAL (from 2nd exon ) | + | + | + | − | − | − | − | − | G Parenti (8) (1995) | |
| 18 | Southern blotting for STS gene PCR for KAL1 gene | STS | − | + (Mild) | + | − | − | − | − | − | |||
| 20 years | 46,XY | PCR using STS and KAL primers | KAL (1st 3 exons ) STS | + | + | + | − | − | − | − | − | Nunez et al (9) (1998) | |
| 13 years | 46,XY | Array-CGH | 5.5 Mb del (X) (p22.31p 22.33) | STS ARSE | − | − | + | − | − | − | + | ADHD | Lonardo et al. (10 ) 2007 |
| FISH for Xp22.32 | No signal | ||||||||||||
| PCR | No amplification | ||||||||||||
| 13.5 years | 46,Y,del (X) (p22.2) | Whole genome 2.7M array | 9.7 Mb deletion at Xp22.2pter | SHOX CDPX1 NLGN4 STS KAL1 GPR143 | + | + | + | + | +(mild) | + | − | Cleft lip ocular albinism rhizomelia with madelung deformity | Cho (11) (2012) |
| 39 years | 46,XY | Microarray based CGH | 4.7Mb loss on Xp22.32 p22.31 | KAL, STS | + | + | + | − | − | − | − | − | Raso et al (12) (2017) |
| 6 months | 46,XY | Microarray based CGH | 2.7Mb loss within Xp22.31 | KAL (exon 8–14), STS | + | + | + | − | − | − | − | Right renal aplasia and left hydronephrosis | Nagai et al. (13) (2017) |
Table 2. Genes deleted due to Xp22.33p22.31 involvement and findings in our patient
| Clinically significant genes | Associated disorder | Findings in our patient |
|---|---|---|
| ANOS1 (exon 7-14) | Kallmann syndrome | Hypogonadotrophic hypogonadism, hyposmia, sykinesia of hands suggestive of Kallmann syndrome |
| STS | Ichthyosis, X-linked | Mild ichthyosis on abdomen and back |
| NLGN4X | Mental retardation, X-linked | Poor scholastic performance and mild intellectual disability |
| ARSE | Chondrodysplasia punctate, X-linked * | No characteristic facies or brachytelephalangy or skeletal findings Short stature and cognitive abnormality is present |
| SHOX # | Short stature, idiopathic familial | No evidence of mesomelia or madelung deformity. |
| Leri-Weill dyschondrosteosis | ||
| Short stature is present | ||
| Langer mesomelic dysplasia |
The characteristic epiphyseal stippling disappears after 3 years of age and other skeletal findings improve by adulthood. Incomplete penetrance seen
Clinical expression is highly variable and becomes more pronounced with age
Moreover, an attempt was made in this study to review the literature to identify the cases of Kallmann syndrome caused by chromosomal aberrations (Table 1). Ballabio et al. (5) were the first group who confirmed the hypothesis of contiguous gene syndrome in deletions involving distal short arm of chromosome X and constructed a disease map of this region. They enrolled 16 male patients showing variable deletions in Xp22-pter region identified on the karyotype and then used specific molecular probes and southern blotting technique to refine the chromosomal region of Kallmann syndrome and other disease genes. However, cytogenetic microarray was employed in only three recently reported cases to confirm the involvement of contiguous genes in this region (Table 1).
The 8.3 Mb deletion on Xp22.3 region in our case is the second largest deletion reported till date amongst the cases of Kallmann syndrome caused by chromosomal aberrations. While majority of cases reported in literature show the complete deletion of KAL1 gene, few case reports have also described partial gene deletions (Table 1) in Kallman syndrome similar to our case.
To conclude, patients presenting with features of Kallmann syndrome should be carefully evaluated for other clinical features like ichthyosis and short stature. This would further help in tailoring the investigational approach for this disorder and screening for other comorbidities.
We thank the patient and his family for their support.
